Showing posts with label FitnessJourney. Show all posts

Monday, October 12, 2026

Creatine Is More Than a Performance Tool–It Supports Recovery, Too

Image by Pure Encapsulations / Contributor for sponsor

At mindbodygreen, we champion proactive wellness as the foundation of strength, resilience, and vitality. A powerful tool that aligns with this philosophy is creatine. Not only is it one of the most studied supplements, but it’s backed by research and known to support a healthy body and brain. So, when you’re taking your fitness routine seriously whether you’re lifting weights or a Pilates regular you can make the most of your investment by optimizing with creatine. Creatine supports muscle strength, performance, and recovery2, which means it can help support recovery………Continue reading….

By:  Mercey Livingston

Source:  Mindbodygreen

.

Critics:

Creatine is a naturally occurring non-protein compound and the primary constituent of phosphocreatine, which is used to regenerate ATP within the cell. 95% of the human body’s total creatine and phosphocreatine stores are found in skeletal muscle, while the remainder is distributed in the blood, brain, testes, and other tissues. The typical creatine content of skeletal muscle (as both creatine and phosphocreatine) is 120 mmol per kilogram of dry muscle mass, but can reach up to 160 mmol/kg through supplementation.

Approximately 1–2% of intramuscular creatine is degraded per day, so people need about 1-3 grams of creatine a day to maintain average (unsupplemented) creatine storage. An omnivorous diet provides roughly half of this value, with the remainder synthesized in the liver and kidneys. Creatine is transported through the blood and taken up by tissues with high energy demands, such as the brain and skeletal muscle, through an active transport system.

The concentration of ATP in skeletal muscle is usually 2–5 mM, which would result in a muscle contraction of only a few seconds. During times of increased energy demands, the phosphagen (or ATP/PCr) system rapidly resynthesizes ATP from ADP with the use of phosphocreatine (PCr) through a reversible reaction catalysed by the enzyme creatine kinase (CK). The phosphate group is attached to an NH center of the creatine.

In skeletal muscle, PCr concentrations may reach 20–35 mM or more. Additionally, in most muscles, the ATP regeneration capacity of CK is very high and is therefore not a limiting factor. Although the cellular concentrations of ATP are small, changes are difficult to detect because ATP is continuously and efficiently replenished from the large pools of PCr and CK. Creatine has the ability to increase muscle stores of PCr, potentially increasing the muscle’s ability to resynthesize ATP from ADP to meet increased energy demands.

Creatine supplementation, when combined with strength training, has been reported in humans to augment training-induced increases in satellite cell content and myonuclei number per muscle fiber, changes that may support increases in muscle fiber size. In a separate study of rehabilitative strength training following immobilization, creatine supplementation was associated with increased muscle MRF4 protein expression; however, whether changes in MRF4 directly mediate myonuclear accretion or hypertrophy remains uncertain.

Genetic defects in the creatine biosynthetic pathway enzymes lead to various severe neurological defects. Defects in the two synthesis enzymes cause L-arginine:glycine amidinotransferase deficiency and guanidinoacetate methyltransferase deficiency. Both biosynthetic defects are inherited in an autosomal recessive manner. Creatine transporter defect, characterized by insufficient transport of creatine to the brain, is caused by mutations in SLC6A8 and is inherited in an X-linked manner.

Creatine is a widely researched dietary supplement that increases muscle phosphocreatine stores; it thus enhances short bursts of high-intensity exercise and facilitates strength adaptations. It is most effective in monohydrate form using a loading phase followed by a maintenance dosing protocol. (Creatine supplements are marketed in ethyl ester, gluconate, monohydrate, and nitrate forms.)

According to a 2018 review article in the Journal of the International Society of Sports Nutrition creatine monohydrate is the most effective nutritional supplement to increase high intensity exercise capacity and muscle mass during training. Creatine use can increase maximum power and performance in high-intensity anaerobic repetitive work (periods of work and rest) by 5% to 15%.

Creatine supplementation exerts positive ergogenic effects on single and multiple bouts of short-duration, high-intensity exercise activities, in addition to potentiating exercise training adaptations. Creatine has no significant effect on aerobic endurance. Creatine supplementation for sporting performance enhancement is considered safe for short-term and long-term use, but there is a lack of safety data for use in children and in pregnancy.

Creatine ,FitnessJourney ,GymGoals ,MuscleGain ,HealthAndFitness ,SportsNutrition ,WorkoutSupplements ,StrengthTraining ,FitnessMotivation ,AthleteLife ,Bodybuilding ,WorkoutTips ,PerformanceEnhancement ,HealthyLifestyle ,NutritionMatters ,FitFam ,InShape ,LeanMuscle ,ExerciseScience

Friday, September 25, 2026

How Long Does It Take To Lose Muscle During A Fitness Break?

Image Credit: Marco VDM / E+ via Getty Images

When you’re sidelined by an injury or taking a well-deserved vacation but want to stay devoted to your fitness gains, you might have a burning question: How long does it take to lose muscle? We’re here to keep you from worrying too much about losing those hard-fought gains: All the strength you’ve built up won’t just suddenly disappear. Keep reading for everything you need to know about the muscle loss timeline and what you can do to preserve as much muscle mass as possible during some time away from your regular strength training routine……….Continue reading…

By Sarah Klein

Source: One Peloton

.

Critics:

The hallmark sign of muscle atrophy is loss of lean muscle mass. This change may be difficult to detect due to obesity, changes in fat mass or edema. Changes in weight, limb or waist circumference are not reliable indicators of muscle mass changes. The predominant symptom is increased weakness which may result in difficulty or inability in performing physical tasks depending on what muscles are affected.

Atrophy of the core or leg muscles may cause difficulty standing from a seated position, walking or climbing stairs and can cause increased falls. Atrophy of the throat muscles may cause difficulty swallowing and diaphragm atrophy can cause difficulty breathing. Muscle atrophy can be asymptomatic and may go undetected until a significant amount of muscle is lost.

Skeletal muscle serves as a storage site for amino acids, creatine, myoglobin, and adenosine triphosphate, which can be used for energy production when demands are high or supplies are low. If metabolic demands remain greater than protein synthesis, muscle mass is lost. Many diseases and conditions can lead to this imbalance, either through the disease itself or disease associated appetite-changes, such as loss of taste due to Covid-19.

Causes of muscle atrophy, include immobility, aging, malnutrition, certain systemic diseases (cancer, congestive heart failure; chronic obstructive pulmonary disease; AIDS, liver disease, etc.), deinnervation, intrinsic muscle disease or medications (such as glucocorticoids). Disuse is a common cause of muscle atrophy and can be local (due to injury or casting) or general (bed-rest).

The rate of muscle atrophy from disuse (10–42 days) is approximately 0.5–0.6% of total muscle mass per day although there is considerable variation between people.[5] The elderly are the most vulnerable to dramatic muscle loss with immobility. Much of the established research has investigated prolonged disuse (>10 days), in which the muscle is compromised primarily by declines in muscle protein synthesis rates rather than changes in muscle protein breakdown.

There is evidence to suggest that there may be more active protein breakdown during short term immobility (<10 days). Certain diseases can cause a complex muscle wasting syndrome known as cachexia. It is commonly seen in cancer, congestive heart failure, chronic obstructive pulmonary disease, chronic kidney disease and AIDS although it is associated with many disease processes, usually with a significant inflammatory component.

Cachexia causes ongoing muscle loss that is not entirely reversed with nutritional therapy.The pathophysiology is incompletely understood but inflammatory cytokines are considered to play a central role. In contrast to weight loss from inadequate caloric intake, cachexia causes predominantly muscle loss instead of fat loss and it is not as responsive to nutritional intervention. Cachexia can significantly compromise quality of life and functional status and is associated with poor outcomes.

Sarcopenia is the degenerative loss of skeletal muscle mass, quality, and strength associated with aging. This involves muscle atrophy, reduction in number of muscle fibers and a shift towards “slow twitch” or type I skeletal muscle fibers over “fast twitch” or type II fibers. The rate of muscle loss is dependent on exercise level, co-morbidities, nutrition and other factors.

There are many proposed mechanisms of sarcopenia, such as a decreased capacity for oxidative phosphorylation, cellular senescence or an altered signaling of pathways regulating protein synthesis, and is considered to be the result of changes in muscle synthesis signalling pathways and gradual failure in the satellite cells which help to regenerate skeletal muscle fibers, specifically in “fast twitch” myofibers.

Sarcopenia can lead to reduction in functional status and cause significant disability but is a distinct condition from cachexia although they may co-exist. In 2016 an ICD code for sarcopenia was released, contributing to its acceptance as a disease entity.Muscle diseases, such as muscular dystrophy, amyotrophic lateral sclerosis (ALS), or myositis such as inclusion body myositis can cause muscle atrophy.

Damage to neurons in the brain or spinal cord can cause prominent muscle atrophy. This can be localized muscle atrophy and weakness or paralysis such as in stroke or spinal cord injury.More widespread damage such as in traumatic brain injury or cerebral palsy can cause generalized muscle atrophy. Injuries or diseases of peripheral nerves supplying specific muscles can also cause muscle atrophy. This is seen in nerve injury due to trauma or surgical complication, nerve entrapment, or inherited diseases such as Charcot-Marie-Tooth disease.

Alain Paul: “I see clothing as an extension of the body and muscle.” Federation de la Haute Couture et de la

.

LosingMuscles ,MuscleLoss ,FitnessJourney ,StrengthTraining ,BodyTransformation ,FitnessMotivation ,HealthAndWellness ,MuscleMaintenance ,WorkoutRoutine ,NutritionTips ,FitnessGoals ,HealthyLifestyle ,MuscleRecovery ,WorkoutTips ,GymLife ,StrengthLoss ,FitnessAwareness ,WellnessWednesday ,PhysicalFitness ,TrainSmart

Leave a Reply

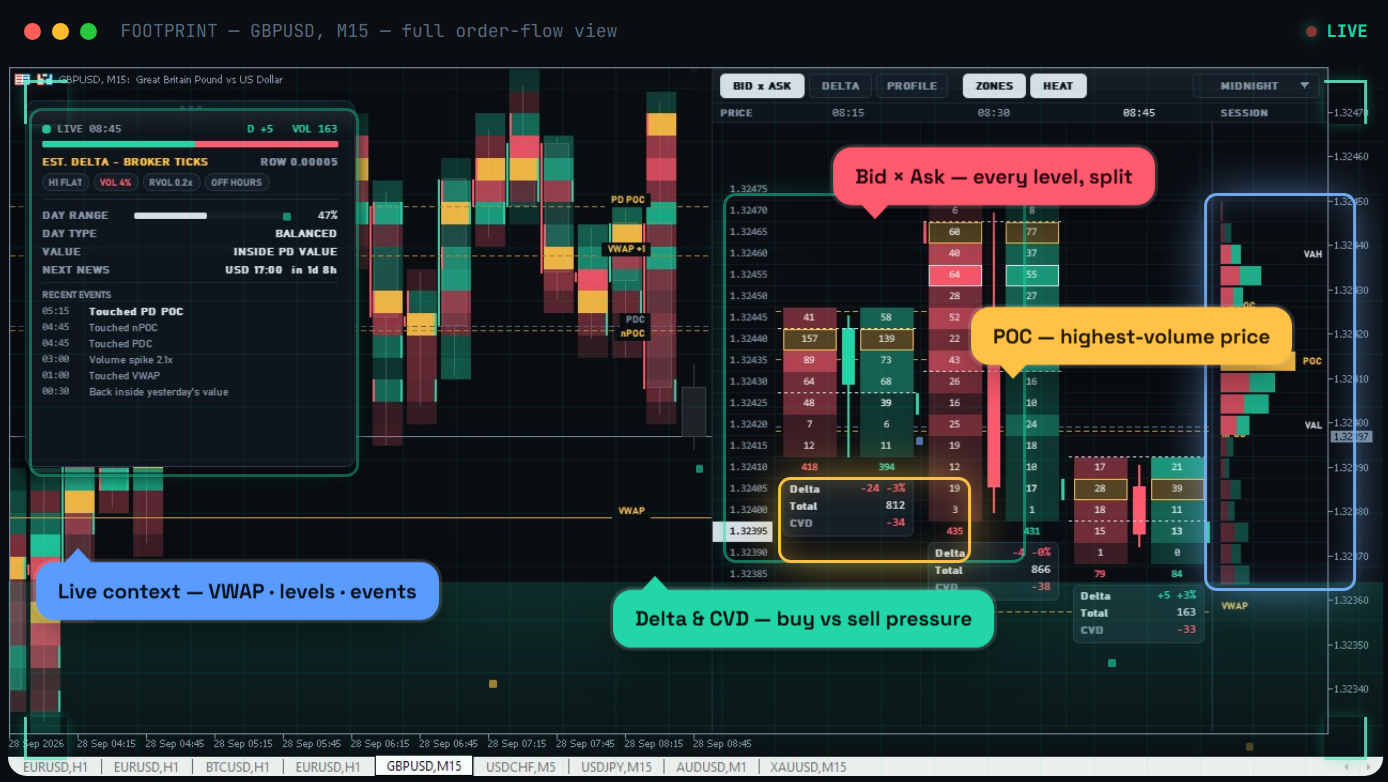
FOOTPRINT Ultimate v2.19 The Trading System For MT4 and MT5 Information

A candle gives you four prices. Open, high, low, close. What it doesn’t show you is what happened in between. How much buying hit each price...